

Self-Medication Prevalence and Practices among Kenyatta University Main Campus Students

Abstract
This study investigated the prevalence of self-medication practices and associated factors among students at Kenyatta University. A cross-sectional survey design was employed, with a structured questionnaire serving as the primary data collection instrument. Data were gathered as of 26 February 2016 at the university’s main campus through a six-month illness recall. A sample of 385(48.8% male; 50.6% female) established using Fischer’s formula, was drawn from the institution’s 35,000 main campus students and recruited as respondents. Simple random sampling, primary data was collected, coded and analyzed using SPSS version 22. The findings indicated that self-medication is high (73.7%), with 84.2% self-medicating manufactured pharmaceuticals while 8.3%used herbal medicine. Respiratory conditions, like cough, cold, sore throat, accounted for more than half (62%) of the symptoms prompting self-medication. The self-medicated drugs were predominantly obtained from pharmacies (78.7%). Among the pharmaceutical drugs, analgesics was the most popular self-medicated class (50.3%). Pharmacists were the primary source of medication information (29.7%). Paracetamol was the predominant analgesic (58.7%). To address the elevated prevalence, the study recommends strengthened regulatory enforcement, targeted student education on the risks of self-medication, and improved access to affordable healthcare services.
Highlights
- ObjectiveNo reliable short passage identified. Please consult the full article. Read full text
- MethodsThe study employed a cross-sectional survey design. Read source
- FindingsThe study found that 8.3% of the respondents used herbal remedies, with commonly cited preparations including Azadirachta indica (neem), Aloe vera, honey, ginger, garlic, lemon, and Moringa oleifera. Read source
- ConclusionThis study reveals self-medication as a dominant health-seeking strategy among Kenya university main campus students, driven by medical training, frequent minor illnesses, and limited insurance access. Read source
About this reading aid
These are complete passages selected automatically from the abstract and full text using section labels and study-specific wording. Selection runs locally on the journal server, without an external AI service. It may miss nuance or select an imperfect passage; it is not an independent assessment or an editor-reviewed summary. Missing points are identified explicitly.
Introduction
Globally, self-care practices encompassing proper nutrition, hygiene, and healthy lifestyles are advocated as strategies to alleviate the burden on public health systems (World Health Organization [WHO], 2022). However, individual and collective self-care behaviors are profoundly influenced by environmental and socioeconomic determinants (Reshna et al., 2021). In numerous societies, the use of over-the-counter (OTC) medications is regarded as an integral component of self-care, as it mitigates illness risk and enhances overall well-being (May et al., 2023). For instance, Noone and Blanchette (2018) report that over 80% of adults in the United States self-medicate with paracetamol/acetaminophen for colds and headaches. Similarly, Mendoza et al. (2025) identify young adults aged 18–25, women, rural dwellers, and low-income populations as exhibiting the highest self-medication rates.
In Africa, self-medication prevalence varies widely, ranging from 12.1% to 93.9%, with the highest rates observed in West and North Africa (Yeika et al., 2021). Makeri et al. (2025) highlight antibiotics such as cotrimoxazole (55.7%), antimalarials (55.3%), analgesics like paracetamol (8.7–62%), herbal remedies (40–50%), and opioids (10%) as the predominant self-medicated agents across the continent. In endemic poverty settings, self-medication emerges as a primary alternative for managing illness, given the unaffordability of formal healthcare services (Noone & Blanchette, 2018). This practice is particularly prevalent in developing countries, where access and affordability of healthcare pose significant public health challenges (May et al., 2023). Sharif (2017) notes that in such regions, individuals frequently resort to a wide array of non-prescribed drugs including herbal medicines, oral antipyretics, antimalarials, and antibiotics procured from local outlets without medical oversight.
The absence of clinical evaluation by qualified providers and the unregulated nature of self-medication heighten vulnerability to multiple risks (Camilleri, 2024). Rusiz (2010) identifies misdiagnosis, inappropriate drug selection, treatment delays, pathogen resistance, and dosage errors as principal hazards. Additional complications include adverse drug reactions, allergies, addiction, drug interactions, and masking of serious underlying conditions (Montastruc et al., 2016). Non-prescribed use of antibiotics and antimalarials has been implicated in antimicrobial resistance (AMR) and parasite resistance, with widespread documentation across nations (Al-Worafi, 2020). In the United States, opioid-related overdoses from self-medication contribute to approximately 130 daily deaths and 1.3 million annual emergency visits (Langabeer et al., 2021), while AMR linked to antibiotic misuse accounts for about 35,000 deaths yearly (Fong, 2023). The WHO has consistently warned of these dangers, particularly antibiotic resistance (Rather, 2017), yet non-prescribed drug use, including OTC agents, persists. Notably, Camilleri (2024) reports that 76% of self-medicating individuals are aware of the risks but proceed regardless.
In Kenya, despite national policy guidelines regulating self-medication, prevalence remains elevated (Kimathi et al., 2022). Commonly self-medicated drugs include antibiotics such as amoxicillin, analgesics like paracetamol, antimalarials, cannabis, and traditional herbal remedies (Owuor, 2022). The COVID-19 pandemic exacerbated self-medication in Africa by 20–40%, with azithromycin emerging as the leading agent (Kimathi et al., 2022). Walekhwa et al. (2022) documented widespread self-medication among Kabarak University students, primarily for respiratory conditions, with elevated risks of analgesic overdose. The present study extends these findings by examining the prevalence of self-medication practices among Kenyatta University students and identifying associated factors.
Methods
Research Design
The study employed a cross-sectional survey design. Ideally, this approach allows the researcher to collect data at a single point in time. For this research, the cross-sectional research design enhanced collection of data that allowed the study to get a snapshot of prevalence of self-medication practices among university students in Kenya.
Study Location and Population
The study was conducted in Kenyatta University Main Campus. The institution is located in Kahawa West location, Githurai Division, Kasarani, Nairobi along the Nairobi–Thika Highway. It is about 17–18 km northeast of Nairobi CBD. Geographically, Kenyatta University Main Campus sits on a 1,000-acre piece of land and accommodates about 35,000 students. Its schools include environmental science, education, business, economics, law, health sciences and pure and applied sciences.
Sample and Sampling Technique
The study population comprised students enrolled at Kenyatta University Main Campus. At the time of study, the campus had approximately 35,000 students studying in various schools. The sample size was established using Fisher’s sample-size formula (Chow et al., 2017). The formula was as follows:
Where:
- n
- required sample size
- Z
- standard normal value for the selected confidence level
- p
- estimated population proportion
- q
- complement of the estimated proportion (1 − p)
- d
- margin of error
Using a 95% confidence level, Z = 1.96, p = 0.50, q = 0.50, and d = 0.05. Fisher’s formula therefore produced a minimum sample size of 384.16, which was rounded up to 385 participants.
A sample of 385 students was picked randomly and recruited as study participants.
Data Collection Instrument
A pretested, semi-structured questionnaire was used to collect the relevant information. Incorporating both open and closed-ended questions allowed gathering of comprehensive information on the subject. The questionnaire was prepared in English.
Data Collection Procedure
Data was collected by administering the questionnaires to respondents randomly. This task was conducted by trained enumerators. Verbal consent was sought from the respondents before being allowed to participate in the study. The questionnaires were completed in the presence of enumerators to assist participants who experienced difficulties during participation.
Data Analysis
Data that was collected was coded accordingly in MS Excel and analysed using Statistical Package for Social Sciences (SPSS), version 22, software. Descriptive and inferential statistics were computed at 95% confidence interval.
Ethical Considerations
Ethical clearance was given by the chairman of therapeutic department in the school of medicine. The study also emphasized respondent confidentiality, anonymity and informed consent. The respondents were assured that any information they gave would be kept secret and used for purposes of the research only. The study also sought all personal identifiers from the questionnaires to ensure anonymity. Verbal permission was also sought from selected respondents before filling of the questionnaires.
Findings
| Factor | Classification | Frequency | Percentage |
|---|---|---|---|
| Gender | Male | 188 | 48.8% |
| Female | 195 | 50.6% | |
| Age | 18-25 | 373 | 96.9% |
| 26-30 | 10 | 0.3% | |
| 31-35 | 2 | 0.18% | |
| School | Medical | 53 | 13.8% |
| Non-medical | 332 | 86.2% |
 From the findings, 284/385 confessed that they had self-medicated in the last 6 months, suggesting that the prevalence of self-medication among the study participants was 73.77%. Students enrolled in medical courses exhibited a higher propensity for self-medication compared to those in non-medical courses. Frequent illness and lack of medical insurance coverage were associated with an increased likelihood of self-medication.
| Practice | Observation | Frequency | Percent |
|---|---|---|---|
| Self-medication frequency in the last 6 months | None | 101 | 26.23% |
| Once | 48 | 12.47% | |
| Twice | 39 | 10.14% | |
| Thrice | 27 | 7.01% | |
| More than thrice | 172 | 44.6% | |
| Classification of self-medicated drugs by origin | Herbal medicine | 24 | 8.3% |
| Pharmaceutical/industrial Medicine | 239 | 84.2% | |
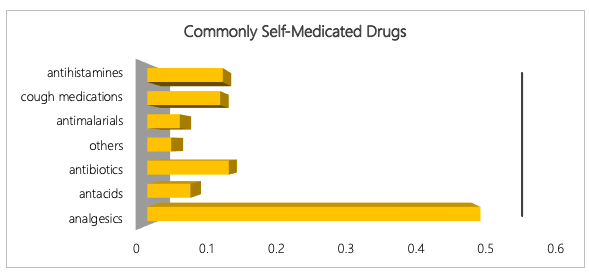
| Pharmacological/therapeutic classification of the self-medicated drugs | Antihistamines | 32 | 11.4% |
| Analgesics | 143 | 50.3% | |
| Cough medications | 31 | 11% | |
| Antimalarial | 14 | 4.9% | |
| Antibiotics | 35 | 12.3% | |
| Antacids | 19 | 6.5% | |
| Other medications | 10 | 3.6% | |
| Symptoms/ailments leading to self-medication | Malaria | 26 | 9% |
| Losing weight | 6 | 2% | |
| Skin conditions | 11 | 4% | |
| UTIs | 6 | 2% | |
| Intestinal disorders | 48 | 17% | |
| Pain | 83 | 29% | |
| Respiratory conditions | 176 | 62% | |
| Sleep disorders | 11 | 4% | |
| Source of the self-medicated drugs | Pharmacy | 224 | 78.7% |
| Family member | 23 | 8.2% | |
| Household stockpiles | 22 | 7.9% | |
| Friends | 5 | 1.9% | |
| Ordinary shops | 9 | 3.3% | |
| Source of information about the self-medicated drugs | Professional training | 2 | 0.6% |
| Advertisements | 29 | 10.2% | |
| Internet search results | 24 | 8.4% | |
| Previous prescription | 31 | 10.7% | |
| Friends | 38 | 13.2% | |
| Family member | 77 | 27.1% | |
| Pharmacist | 85 | 29.7% |
The study found that 8.3% of the respondents used herbal remedies, with commonly cited preparations including Azadirachta indica (neem), Aloe vera, honey, ginger, garlic, lemon, and Moringa oleifera. In contrast, the majority (84.2%) used manufactured pharmaceuticals for self-medication. Respiratory conditions, like cough, cold, sore throat, accounted for more than half (62%) of the symptoms prompting self-medication. Additional conditions included painful symptoms, including headache, backache, dysmenorrhea, and arthritic pain; gastrointestinal disorders (constipation, nausea, vomiting, and heartburn; 17%), malaria (9%), and a residual 10% comprising urinary tract infections, skin infections, sleep disorders, and weight loss.
Among self-medicated drugs, analgesics were the most popular, constituting 50.3% of the cases of self-medication. Antibiotics followed at the rate of 12.3%. The study also found high prevalence of antihistamine self-medication (11.4%), and cough medications (11.0%), antacids (6.5%), and antimalarials (4.9%). Other categories included levonorgestrel emergency contraception (Postinor-2), corticosteroids (e.g., extraderm, mediven, prednisolone), anthelmintics (e.g., albendazole), and antispasmodics like buscopan. Paracetamol was the predominant analgesic (58.7%), followed by non-steroidal anti-inflammatory drugs (NSAIDs; 21.9%) and Mara Moja (17.4%). Among NSAIDs, ibuprofen was most frequently reported (47.1%). Amoxicillin was the leading antibiotic (26.3%), followed by cotrimoxazole (23.7%), with erythromycin and doxycycline also noted. Artemether-lumefantrine dominated antimalarial use (80%), with 20% unspecified. Eno and Actal were the primary self-medicated antacids. Chlorpheniramine was the most common antihistamine (62.9%), followed by cetirizine (28.6%) and celestamine (8.6%). Among respiratory medications, Flugone was predominant (29.4%), followed by Cold Caps (23.5%), cough syrups (17.6%), and Strepsils (20.6%).
Medications were predominantly obtained from pharmacies (78.7%), with smaller proportions sourced from family (8.2%), friends (1.9%), household stockpiles (7.9%), or retail shops (3.3%). Pharmacists were the primary source of medication information (29.7%; 128/431), followed by family members (27.1%) and friends (13.2%). The respondents also sourced medication information from previous prescriptions (10.7%), the internet, advertisements, and general/professional training (0.6%).
Discussion
The self-medication prevalence and practices among Kenyatta University Main Campus Students as observed in this study underscore a pervasive engagement in autonomous therapeutic decision-making. The findings align with Walekhwa et al. (2022), who indicated that self-medication is common among university students. The study found that medical students engage in self-medication more than their non-medical counterparts. This disparity aligns with the concept of health literacy and professional socialization theory, wherein medical training fosters familiarity with pharmacodynamics, symptomatology, and drug nomenclature, thereby reducing perceived barriers to self-diagnosis and treatment. Salisu et al. (2019) aver that this enculturation inadvertently normalizes self-medication as an extension of clinical reasoning, even outside supervised contexts.
Frequent illness and absence of medical insurance emerge as significant self-medication predictors, resonating with Andersen’s Behavioral Model of Health Services Use. Graham et al. (2017) indicate need factors, especially recurring morbidity and enabling factors (financial inaccessibility) converge to propel the students toward self-medication as a pragmatic adaptation. Based on Bryan (2018), this also reflects a broader rational choice framework, which underscores the tendency of people to weigh time, cost, and convenience against formal healthcare, translating to prioritization of immediacy over evidence-based protocols.
The symptom profile associated with self-medication, dominated by respiratory and pain-related complaints mirrors global patterns documented in self-medication literature and aligns with lay epistemologies of illness (Fitzpatrick, 2022). People construe minor, self-limiting conditions as manageable through experiential or culturally embedded knowledge, diminishing the perceived necessity for professional healthcare provider consultation. Conversely, from Van der Linden and Schermer’s (2022) viewpoint, the inclusion of malaria and gastrointestinal disorders hints at contextual disease burden, where endemicity and familiarity breed confidence in over-the-counter or previously prescribed regimens.
The predominance of manufactured pharmaceuticals over herbal remedies suggests a biomedical hegemony in therapeutic preference, even within self-care paradigms. Analgesics, particularly paracetamol, dominate, consistent with their ubiquitous availability, perceived safety, and cultural framing as first-line palliatives. The notable use of antibiotics, however, raises concerns within the antimicrobial stewardship discourse (Brown, 2023). Self-initiated antibiotic therapy, often informed by pharmacists or social networks rather than microbiological evidence, exemplifies diagnostic substitution and contributes to selection pressure for resistance, reflecting a public health externality of individual agency as suggested by Cowen and Schliesser (2024).
Drug acquisition patterns reinforce the pharmacy-centric model of self-medication in resource-constrained settings. Community pharmacies function as quasi-clinics, dispensing not only drugs but also diagnostic legitimacy (Cowen & Schliesser, 2024). Household stockpiles and informal exchanges further embed self-medication within domestic health economies, blurring boundaries between prescribed and autonomous use. Information sources underpinning self-medication further reflect social cognitive theory dynamics. Pharmacists, as accessible health intermediaries, serve as de facto gatekeepers in the absence of physicians, blending professional authority with commercial influence. Peer and familial networks, meanwhile, perpetuate therapeutic mimicry, where past outcomes reinforce future choices irrespective of clinical validity. The marginal role of digital or professional training sources underscores a gap between information availability and critical appraisal competency.
Conclusion
This study reveals self-medication as a dominant health-seeking strategy among Kenya university main campus students, driven by medical training, frequent minor illnesses, and limited insurance access. The preference for manufactured drugs, especially analgesics and antibiotics, sourced primarily from pharmacies and informed by pharmacists or social networks, reflects a blend of biomedical trust and pragmatic autonomy. While empowering, these practices risk misdiagnosis, adverse effects, and antimicrobial resistance, underscoring the tension between individual agency and public health imperatives. Theoretically, findings align with health literacy, professional socialization, and Andersen’s model, highlighting how knowledge, need, and structural barriers shape medicine access and use behavior. In resource-constrained settings, pharmacies are pivotal. However, they may turn into unregulated nodes in the self-care ecosystem.
To mitigate harms, integrating accessible formal care with guided autonomy can serve as a viable path forward, ensuring student empowerment does not compromise safety or societal well-being. Medical use and control interventions should emphasize drug advertisement and pharmacy oversight, expand insurance coverage to improve healthcare access among the vulnerable populations, and embed responsible self-medication education within curricula.
References
Rights and permissions

Disclaimer
All claims expressed in this article are solely those of the author and do not necessarily represent those of the publisher, editors, reviewers, or affiliated institutions. Any product, service, or claim that may be evaluated in this article is not guaranteed or endorsed by the publisher.
Publisher’s note
The publisher remains neutral with regard to jurisdictional claims.
Declarations & editorial transparency
Data availability
Peer review statement HRL Journal Service Policy
HRL Journal Service uses the following process for manuscripts sent for external peer review. An associate editor screens scope and eligibility; an academic editor assesses subject relevance and scholarly quality. The Editor-in-Chief and academic editor appoint suitable reviewers and manage conflicts of interest. Review is double blind: author and reviewer identities are concealed from one another during review. Authors respond to the feedback, with further review where needed. Once satisfied with the revisions, the academic editor recommends approval and forwards the manuscript for copyediting, reference checks and correction of typographical errors. The Editor-in-Chief makes the final publication decision. Article-specific review records and any exceptions are reported separately below.
Article-specific review status not recorded
Academic editor names are published according to the journal’s disclosure policy and the editor’s consent. An editor may request non-display; authors may raise a reasoned concern, which the journal assesses for privacy, safety and conflicts of interest. A missing name alone does not establish the reason for non-display or imply an ethics concern. Reviewer anonymity during double-blind review is a separate matter.
AI use & language assistance HRL Journal Service Policy
Authors and copyeditors may use language-assistance tools, including Grammarly, to improve spelling, grammar and readability under human supervision. Edits must preserve scientific meaning, uncertainty and the authors’ interpretation. Authors remain responsible for the accuracy, originality, references and integrity of their work; AI tools cannot qualify as authors or replace editorial judgement. Authors must disclose AI assistance at submission. Generative rewriting, content creation or use in research methods, analysis or figures requires an article-specific statement identifying the tool and its purpose; no use may fabricate data, sources or findings. Confidential manuscripts and personal data must not be shared with external tools without appropriate permission and confidentiality safeguards. This shared policy does not establish whether a tool was used in this article; any supplied article-specific disclosure appears below.
No separate AI-use disclosure has been supplied in this record. This does not establish that AI was or was not used.
Publication timeline
Recorded milestones for this article. Only supplied dates are shown.
- Received
- Revised
- Accepted
- Published
How the HRL review process works
The standard route for manuscripts sent for external peer review; this illustration does not certify individual stages or supply missing dates.
- 01Scope & eligibilityAssociate editor
- 02Subject assessmentAcademic editor
- 03Double-blind peer reviewReviewers appointed by the editorial team
- 04Revisions & academic approvalAuthors respond; academic editor evaluates
- 05Copyediting & reference checksCopyeditor
- 06Final publication decisionEditor-in-Chief
Cite this article
Share this article
Share the article record with colleagues and readers worldwide.
Explore research across our journalsDiscover more research

Recent Publications

Most Read

Recommended
Save this article as a bookmark
Use your browser’s secure bookmark shortcut. Both desktop options are shown below.
Press Ctrl+D
In Chrome, Edge or Firefox, choose a folder if needed, then select Done.
Press ⌘ Command+D
In Safari, Chrome or Firefox, choose the bookmark location and confirm.
Add to Mendeley
Save this article’s reference using either option below.
Import a reference file
Download the RIS file, then import it in Mendeley Reference Manager using Add new → Import library, or drag the file into your library.
Download RIS for MendeleyUse Mendeley Web Importer
With the extension installed, return to this article and select the Mendeley icon in your browser toolbar. Review the detected reference before saving.
Get the official Web ImporterYou choose what to import. Opening this dialog does not sign you in or send article content to Mendeley.
Cite this article
Copy a formatted citation or download a reference file.
Cited by
Crossref citation count for this DOI.